

Table of Contents
- What Is PEMF Therapy for Urinary Incontinence
- Understanding Urinary Incontinence: Types and Symptoms
- How Electrical Stimulation for Urinary Incontinence Differs from PEMF
- PEMF Therapy Research for Bladder Leakage: What the Evidence Shows
- Pelvic Floor Physiotherapy for Urinary Incontinence and PEMF Integration
- Urinary Incontinence Treatment Options: Where PEMF Fits
- Treatment Protocol, Realistic Expectations, and Safety Considerations
- Frequently Asked Questions
Last Updated: October 12, 2026
What Is PEMF Therapy for Urinary Incontinence
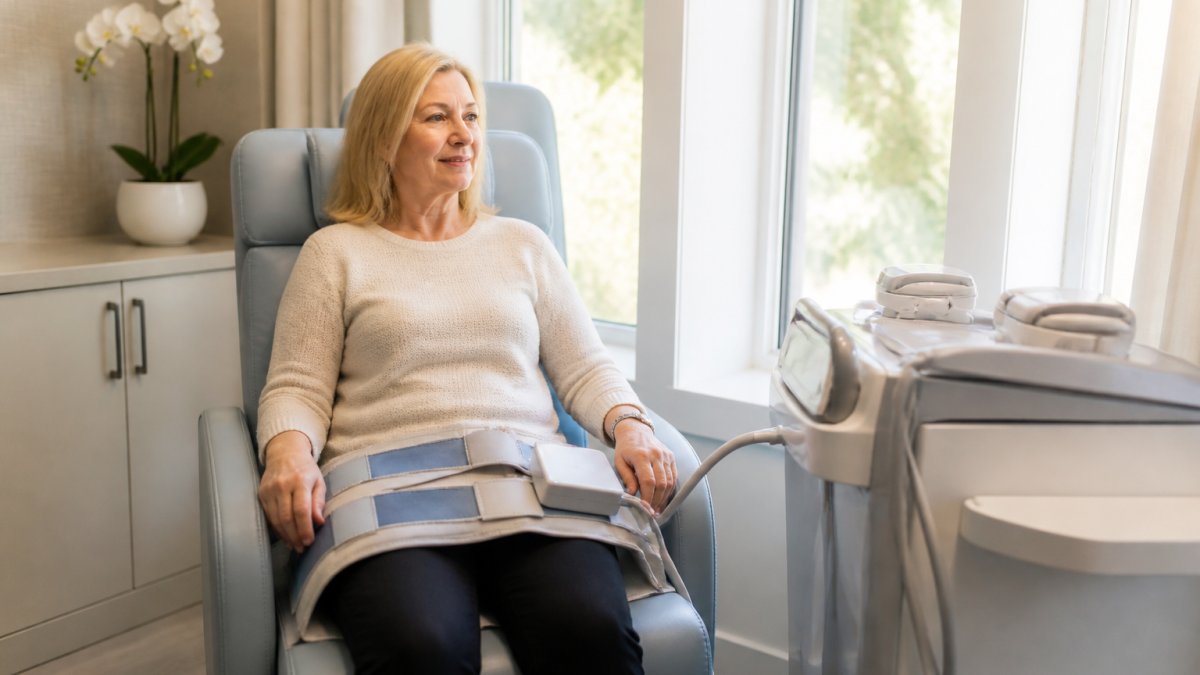
Pulsed electromagnetic field (PEMF) therapy is a non-invasive treatment that uses electromagnetic pulses to stimulate pelvic floor muscles and nerves, helping to reduce urinary incontinence symptoms. Delivered through a device placed against the skin, it allows patients to remain fully clothed while strengthening pelvic floor function and improving bladder control without pharmaceutical side effects or recovery time.
At Core to Floor, we’ve integrated PEMF therapy into our clinical practice because the evidence supporting its use for urinary incontinence continues to grow. Our approach is supervised by the Barrie Urology Group, ensuring treatment protocols are safe and evidence-based. Many patients find it appealing as a conservative first step before more invasive options, especially for stress urinary incontinence, urge incontinence, or mixed presentations.
How PEMF Stimulation Works on Pelvic Floor Muscles and Nerves
PEMF therapy operates through a mechanism that targets the neuromuscular system controlling bladder function. The electromagnetic pulses stimulate nerve fibers in the pelvic region, triggering muscle contractions in the pelvic floor. These contractions strengthen the muscles responsible for maintaining continence and supporting pelvic organs.
The pelvic nerves that control urinary function respond by increasing their activity and improving communication between the bladder, sphincter muscles, and the brain.
A key difference between PEMF therapy and other electromagnetic approaches is that PEMF uses pulsed rather than continuous fields. This pulsing pattern is designed to optimize pelvic floor response without discomfort.
Understanding Urinary Incontinence: Types and Symptoms
Urinary incontinence is the involuntary loss of urine, ranging from occasional light leakage to complete loss of bladder control. Identifying which type you experience is essential because treatment approaches differ based on the underlying cause, and accompanying lower urinary tract symptoms (LUTS) can significantly affect quality of life and daily activities.
Stress Urinary Incontinence
Stress urinary incontinence occurs when physical activity, coughing, sneezing, exercising, or laughing, causes urine leakage. This happens because the pelvic floor muscles and urethral sphincter are unable to generate sufficient pressure to prevent urine escape during increased abdominal pressure.
Symptoms range from light spotting during intense exercise to noticeable leakage during everyday activities, leading many people to avoid activities or use protective pads. Men can also experience stress urinary incontinence, particularly after prostate surgery or radiation therapy, though it is less common than in women.
PEMF therapy addresses stress urinary incontinence by strengthening the pelvic floor muscles responsible for supporting the urethra and sphincter. Stronger muscles generate greater pressure during moments of increased abdominal strain, reducing or eliminating leakage episodes.
Urge Urinary Incontinence and Overactive Bladder
Urge urinary incontinence is characterized by a sudden, compelling urge to urinate followed by involuntary urine loss.
Overactive bladder symptoms can be severely limiting, affecting sleep, work productivity, and social participation. Causes include neurogenic bladder dysfunction, where nerve signals between the bladder and brain become dysregulated, as well as bladder pain syndrome (interstitial cystitis) or irritation from various sources.
PEMF therapy for urge incontinence works by modulating sacral nerve activity and reducing abnormal bladder contractions. By stabilizing nerve signaling, PEMF therapy can help normalize the bladder’s response to filling, reducing the frequency of urgent episodes and improving symptom control.
Mixed Urinary Incontinence
Mixed urinary incontinence combines features of both stress and urge incontinence: leakage during physical activity or increased abdominal pressure AND involuntary loss associated with sudden urges. This combination is common, particularly in women navigating perimenopause or menopause, and in aging adults of both sexes.
Treatment of mixed incontinence is more complex because it requires addressing both the structural support of the pelvic floor and the neurological regulation of bladder contractions. PEMF therapy’s dual mechanism, strengthening muscle tone while modulating nerve signaling, makes it particularly suited to managing mixed presentations.
How Electrical Stimulation for Urinary Incontinence Differs from PEMF
Electrical stimulation and PEMF therapy are distinct technologies, though both work through neuromuscular stimulation. Understanding the differences helps clarify why PEMF may be appropriate for certain patients and situations.
Electrical stimulation uses direct electrical current applied through electrodes placed on or inside the body, triggering muscle contractions and nerve responses.
PEMF therapy, by contrast, uses pulsed magnetic fields that do not require direct contact with skin or penetration into body tissues.
The key practical difference: electrical stimulation often produces visible or felt muscle contractions because current flows directly through tissue, while PEMF therapy works more subtly, with mild sensations and fewer dramatic visible contractions.
Research suggests the two may work through complementary mechanisms. Some practitioners combine both for moderate-to-severe symptoms.
PEMF Therapy Research for Bladder Leakage: What the Evidence Shows
Research into PEMF therapy for urinary incontinence has grown substantially over the past decade. A 2022 randomised controlled trial examined women with stress urinary incontinence who combined PEMF therapy with standard pelvic floor training.
This suggests PEMF therapy is not a replacement for pelvic floor training but an effective adjunct.
Research into PEMF therapy for urge incontinence and overactive bladder is emerging but less extensive than stress incontinence studies. Available evidence indicates PEMF therapy can reduce urinary frequency and urgency episodes, though improvement varies between individuals.
Clinical trials examining PEMF therapy have generally reported good safety profiles, with minimal adverse effects and high patient tolerance, and most describe improvements in symptom severity, quality of life, and patient satisfaction.
The strongest evidence for PEMF therapy exists for stress urinary incontinence when combined with pelvic floor training, showing significantly greater strength gains and symptom reduction than training alone.
Pelvic Floor Physiotherapy for Urinary Incontinence and PEMF Integration
Pelvic floor physiotherapy, often called pelvic floor physical therapy or pelvic floor muscle training, remains the first-line conservative treatment for most types of urinary incontinence.
A qualified pelvic floor physiotherapist assesses muscle strength, coordination, and endurance through manual examination, sometimes using biofeedback or ultrasound imaging. Treatment typically involves daily exercises progressed over 8-12 weeks or longer depending on severity and response.
PEMF therapy integrates well with pelvic floor physiotherapy because both target the same musculature and neural pathways. Physiotherapy provides active muscle training and patient education, while PEMF therapy provides passive neuromuscular stimulation that accelerates adaptation.
At Core to Floor, we emphasize that PEMF therapy complements rather than replaces physiotherapy.
Urinary Incontinence Treatment Options: Where PEMF Fits
Incontinence treatment exists on a spectrum from conservative to invasive, and the choice depends on symptom severity, patient preference, underlying cause, and response to initial interventions. PEMF therapy occupies an important position in this spectrum as a non-invasive, conservative option that bridges the gap between pelvic floor training alone and surgical intervention.
Conservative and Behavioral Approaches
Behavioral modifications form the foundation of incontinence management. Fluid management can reduce urinary frequency and urgency, bladder training gradually extends the time between urination to improve capacity and reduce overactive contractions, and pelvic floor exercises strengthen muscles that support continence.
Lifestyle modifications including weight management, reduced caffeine and alcohol intake, and treating chronic cough can significantly improve symptoms, and for mild incontinence these conservative approaches alone may be sufficient.
PEMF therapy enhances conservative management by accelerating pelvic floor strengthening and improving nerve function.
Surgical and Minimally Invasive Interventions
When conservative approaches do not produce adequate relief, surgical and minimally invasive options become relevant. For stress urinary incontinence, mid-urethral slings are the most common procedure, providing mechanical support to the urethra and sphincter. Success rates are high, but surgery carries risks including infection, bleeding, and urinary retention.
For urge incontinence and overactive bladder, options include sacral neuromodulation, botulinum toxin injection into the bladder muscle, or anticholinergic medications. These are effective but carry their own risks and side effects.
PEMF therapy serves as a conservative stepping stone before surgery. Combined with pelvic floor training, it offers a legitimate opportunity for meaningful improvement without surgical risk, and often succeeds for mild-to-moderate symptoms.
PEMF therapy is not appropriate as a sole treatment for severe incontinence or for patients with anatomical abnormalities requiring surgical correction. A medical evaluation is essential to rule out conditions requiring urgent intervention.
Treatment Protocol, Realistic Expectations, and Safety Considerations
Understanding what to expect from PEMF therapy, including session structure, timeline, and realistic outcomes, helps patients make informed decisions and maintain realistic expectations.
Session Frequency and Treatment Duration
PEMF therapy sessions typically last 15-30 minutes. A typical initial course spans 12 weeks.
After the intensive phase, maintenance sessions may be scheduled once or twice weekly to sustain improvements. The exact protocol varies by incontinence type, severity, and individual response.
Realistic expectations are important: PEMF therapy rarely produces complete continence immediately. Patients typically experience gradual reduction in incontinence episodes, decreased urgency, and improved quality of life.
Consistency matters significantly with PEMF therapy. Patients who maintain the recommended session frequency and combine treatment with pelvic floor exercises tend to achieve better outcomes than those with sporadic attendance or no adjunct training.
Risks, Contraindications, and When to Seek Medical Guidance
PEMF therapy is generally well-tolerated with a favorable safety profile.
Contraindications include active implanted electronic devices such as pacemakers, implantable cardioverter-defibrillators (ICDs), or neurostimulators, since electromagnetic fields may interfere with device function.
Pregnancy is a relative contraindication; while PEMF therapy is not known to harm pregnancy, safety data is limited and most clinicians recommend deferring until postpartum.
A thorough evaluation by a qualified urologist or urogynecologist before starting PEMF therapy ensures the treatment is appropriate for your situation and that underlying conditions are identified and addressed.
Urinary incontinence affects millions of people and often goes untreated due to embarrassment or the assumption that surgery is the only effective option.
Frequently Asked Questions
How does PEMF therapy work for urinary incontinence?
PEMF therapy uses pulsed electromagnetic fields to stimulate pelvic floor muscles and the nerves that control bladder function. These electromagnetic pulses cause muscle contractions, strengthening the pelvic floor and improving nerve signaling to the bladder. A 2022 randomised trial showed that women who combined PEMF with pelvic floor training gained significantly more strength and reported substantially less leakage than those training alone, suggesting PEMF enhances the body’s natural ability to regain bladder control.
What is the difference between PEMF therapy and electrical stimulation for urinary incontinence?
Both use stimulation to strengthen pelvic floor muscles, but they differ in mechanism and application. Electrical stimulation delivers direct electrical current through electrodes, often placed internally or on the skin, causing immediate muscle contraction. PEMF therapy uses magnetic pulses that penetrate tissue without direct electrical contact, allowing treatment while fully clothed. PEMF may also influence nerve function at a deeper level. The choice depends on individual comfort, medical history, and clinical recommendation.
Can pelvic floor physiotherapy combined with PEMF therapy actually work for moderate-to-severe incontinence?
Yes. Pelvic floor physiotherapy alone strengthens muscles through guided exercises, while PEMF adds electromagnetic stimulation to enhance muscle activation and nerve response. Combined approaches address both muscle weakness and nerve dysfunction. Research indicates that adding PEMF to standard pelvic floor training produces better outcomes than training alone. However, severe cases involving anatomical damage or neurogenic bladder may require additional evaluation to determine if PEMF is appropriate alongside or instead of other interventions.
What does research say about PEMF therapy for treating urinary incontinence?
Clinical trials, including a 2022 randomised controlled trial, demonstrate that PEMF therapy reduces urinary frequency, decreases incontinence episodes, and improves quality of life. Studies show particular benefit for stress urinary incontinence and overactive bladder symptoms. While evidence is growing, larger long-term studies are still needed to establish optimal protocols and compare outcomes across different incontinence types and populations.
How often do I need PEMF therapy sessions, and how long does each one take?
Typical PEMF therapy protocols involve 15-minute sessions delivered twice daily over a 12-week treatment period. Some protocols may vary based on individual response and clinical assessment. Sessions are non-invasive and allow you to remain fully clothed, making them easy to fit into daily routines. Your healthcare provider will discuss the specific frequency and duration recommended for your condition during your initial consultation.
Are there any risks or contraindications to PEMF therapy for urinary incontinence?
PEMF therapy is generally well tolerated with a favorable safety profile. However, it may not be suitable for individuals with certain implanted devices (pacemakers, metal implants), active infections, or specific neurological conditions. Pregnancy requires medical clearance. Mild side effects such as temporary tingling or muscle soreness can occur. Always discuss your full medical history with a qualified healthcare provider before starting PEMF therapy to ensure it is safe and appropriate for your situation.